Myopia Control Prediction Calculator: See Your Child’s Vision Future Before It Happens

Nish Fofaria • 18 February 2026

Myopia (short-sightedness) is increasing at an alarming rate worldwide. Children are developing myopia at younger ages, and prescriptions are progressing faster than ever before.


But what if you could predict how your child’s eyesight may change — and take action early?


At Eyecare Opticians, we are proud to introduce our Myopia Control Prediction Calculator, an advanced clinical tool designed to help pares understand potential vision progression and make informed decisions about treatment.


👉 Use the calculator now:

https://www.eyecareopticians.com/specialist-services


Because when it comes to myopia, early understanding leads to better long-term outcomes.


What Is the Myopia Control Prediction Calculator?


The Myopia Control Prediction Calculator is a clinically informed tool that estimates how a child’s prescription could progress over time using key risk indicators.


Within seconds, the calculator generates an easy-to-understand projection — helping parents visualise the possible long-term impact of myopia and the benefits of early intervention.


Think of it as a vision forecast for your child.


Not to alarm — but to empower.


Modern eye care is no longer just about correcting sight. It is about protecting lifelong eye health.


How Does the Prediction Work?


Our calculator goes beyond basic estimates by analysing clinically meaningful data points to build a clearer picture of how your child’s vision may develop.


We assess several important indicators, including:


Current prescription – Children who begin with a higher level of myopia often experience faster progression.


Age – The younger a child becomes myopic, the greater the likelihood that myopia will continue to increase through the growing years.


Axial length – One of the most important measurements in modern myopia management, axial length tracks the physical growth of the eye. As the eye elongates, myopia typically increases. Monitoring this measurement allows us to detect progression earlier and manage it more proactively.


By evaluating these factors together rather than in isolation, we can better forecast risk and recommend intervention at the stage where it can make the greatest difference.


Why Predicting Myopia Matters


Myopia is not simply about needing stronger glasses each year.


Higher levels of myopia are associated with an increased lifetime risk of serious eye conditions such as retinal detachment, glaucoma, myopic macular degeneration, and early cataracts.


While these risks are uncommon in childhood, managing myopia early can significantly reduce the likelihood of eye health complications later in life.


The earlier we act, the greater our ability to influence long-term visual outcomes.


What Makes This Calculator Different?


Many online tools provide broad, generic estimates. Our calculator is grounded in clinical insight and reflects the way modern myopia management is practiced.


It helps parents:


  • Understand possible future prescription ranges
  • See the potential impact of delaying treatment
  • Explore how myopia control can slow progression
  • Make confident, informed decisions


For many families, the greatest benefit is clarity.


No guessing.

No waiting for the next prescription increase.

Just proactive, expert-led care.


How Do Myopia Control Treatments Work?


Modern myopia management focuses on slowing the growth of the eye rather than simply correcting blurred vision.


A range of evidence-based treatments are available, each working in different ways:


Specialist contact lenses create peripheral retinal signals that help reduce the stimulus for eye growth.


Orthokeratology (overnight lenses) gently reshape the front surface of the eye during sleep, allowing clear daytime vision while helping to slow eye elongation.


Myopia control spectacle lenses use advanced optical designs to influence how light focuses across the retina.


Low-dose atropine eye drops may be recommended in certain cases to further help regulate eye growth.


Every child is unique, which is why treatment recommendations are always tailored to the individual rather than adopting a one-size-fits-all approach.


Why Combination Therapy Often Delivers Better Outcomes


Some children respond extremely well to a single treatment. Others — particularly those at higher risk of progression — benefit from a more advanced strategy.


Using a combination of therapies allows us to influence myopia progression through multiple mechanisms. For example, optical treatments may be paired with low-dose atropine to create a stronger overall management effect.


This layered, proactive approach aims not just to manage myopia, but to significantly reduce the likelihood of high prescriptions in adulthood.


Quite simply:


Earlier intervention provides greater opportunity to protect your child’s long-term eye health.


Who Should Use the Calculator?


The tool is particularly valuable for parents who:


  • Have noticed their child’s prescription increasing each year
  • Have a family history of myopia
  • Want to reduce the risk of high prescriptions later in life
  • Prefer proactive healthcare decisions
  • Value expert clinical guidance


Even if your child has just been prescribed their first pair of glasses, this is an ideal time to understand what may lie ahead.


In myopia management, earlier is always better.


What Happens After You Use the Tool?


The calculator is the first step — not a diagnosis.


After reviewing your child’s results, we recommend booking a comprehensive Myopia Assessment. During this appointment we:


  • Perform advanced clinical measurements, including axial length
  • Assess progression risk
  • Discuss suitable treatment options
  • Build a personalised management plan


Our goal is simple:


To help protect your child’s vision for decades to come.


Try the Myopia Control Prediction Calculator Today


Your child’s future eyesight is too important to leave to chance.


Take just one minute to gain clarity and confidence about their visual future.


👉 Click below to use the calculator:

https://www.eyecareopticians.com/specialist-services


Small action today can create a meaningful difference tomorrow.

by Nish Fofaria • 4 September 2026
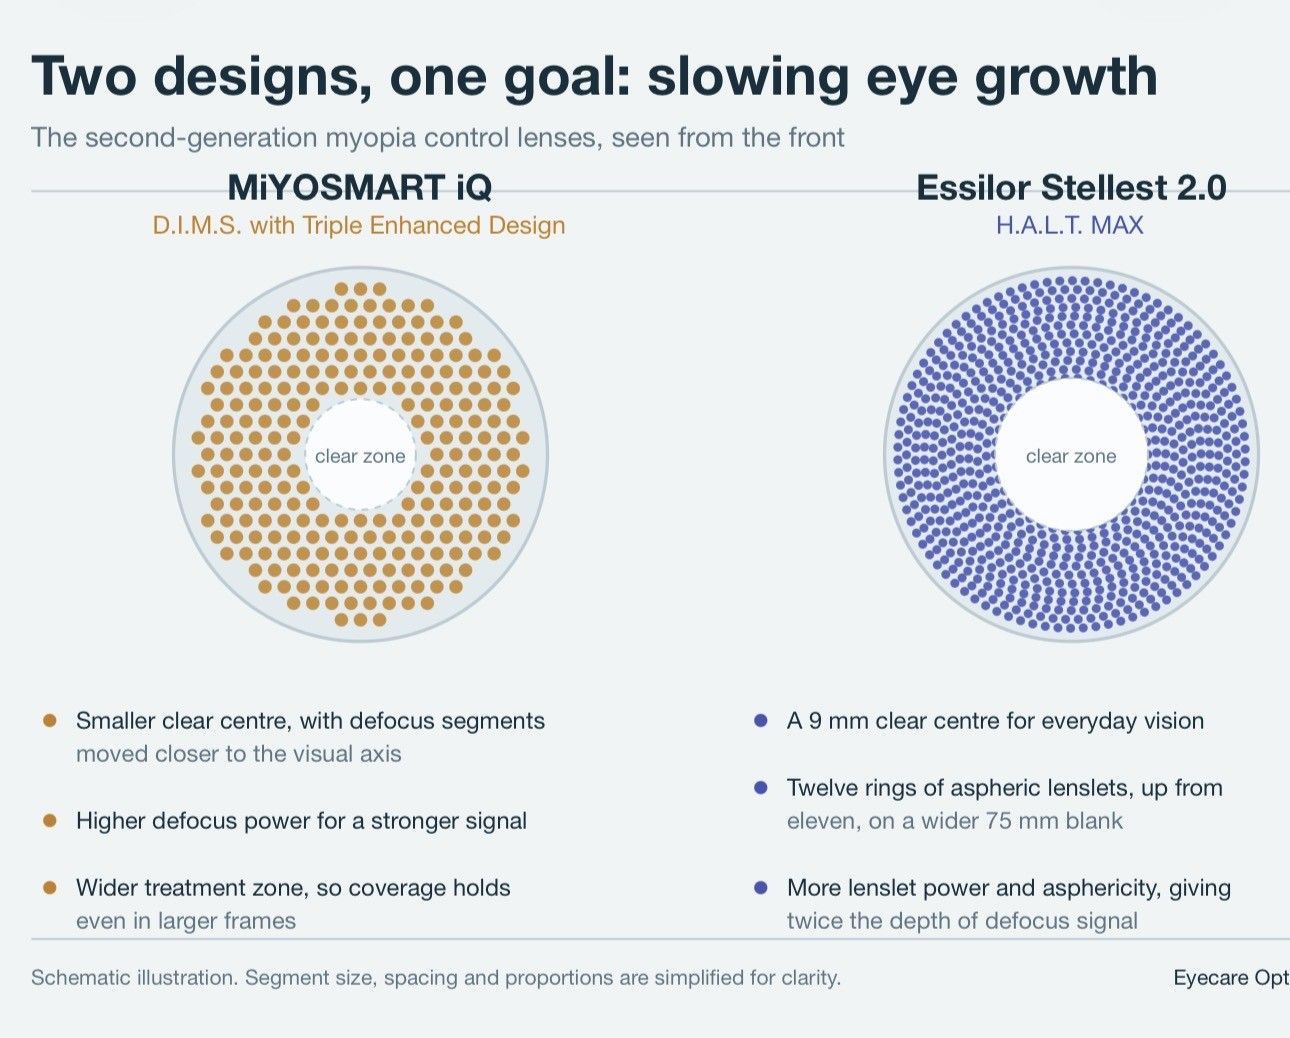
For the last few years, parents of short-sighted children have essentially had two leading spectacle options: HOYA's MiYOSMART and Essilor's Stellest. Both are well evidenced, both slow the eye from growing too long, and both have quietly changed how we manage childhood myopia in practice. In 2025–2026, both manufacturers released second-generation designs — **MiYOSMART iQ** and **Essilor Stellest 2.0**. The headline claims are striking. Here's what has actually changed, what the evidence shows, and how we're thinking about it clinically. First, a reminder of why this matters Myopia isn't just a prescription problem. As a child's eye grows longer, the risk of sight-threatening conditions in adult life rises — retinal detachment, myopic maculopathy, glaucoma and early cataract. Every fraction of a millimetre of axial elongation we prevent in childhood is a permanent reduction in that lifetime risk. Ordinary single-vision glasses correct blur. They do nothing to slow the underlying growth. That distinction is the whole reason myopia control lenses exist. MiYOSMART iQ — HOYA's Triple Enhanced Design The original MiYOSMART, developed with The Hong Kong Polytechnic University, uses D.I.M.S. technology: a clear central zone for the prescription, surrounded by a honeycomb of tiny defocus segments that sit in front of the peripheral retina and signal the eye to slow its growth. MiYOSMART iQ keeps that principle and refines it in three ways — what HOYA calls the **Triple Enhanced Design (DIMS TED)**: 1. **A smaller central clear zone**, with the defocus segments moved closer to the visual axis, so the near-peripheral retina is stimulated more continuously. 2. **Higher defocus power**, producing a stronger treatment signal. 3. **An extended treatment zone**, keeping coverage consistent even in the larger frames children actually want to wear. What the data says At ARVO 2026 in Denver, HOYA and PolyU presented 12-month results from a randomised controlled trial in 196 children: - Roughly **nine out of ten children showed no clinically relevant myopia progression** over the first year of wear. - Across the whole group, mean spherical equivalent changed by **+0.155 D with iQ versus –0.511 D** in single vision, with axial length changing **0.019 mm versus 0.310 mm**. - In children aged **four to six** — a group myopia control lenses have rarely been tested in — efficacy was **65% for refractive error and 44% for axial length**, with mean changes of –0.220 D and 0.266 mm versus –0.635 D and 0.475 mm in single vision. - Earlier six-month interim data suggested iQ was around **twice as effective as the original MiYOSMART** at controlling both progression and eye growth. The evidence in four- to six-year-olds is arguably the most important part. Early-onset myopia progresses fastest and carries the highest lifetime risk, and until now we have had very little lens data in that age group. Essilor Stellest 2.0 — H.A.L.T. MAX Stellest takes a different optical route. Its **H.A.L.T.** technology (Highly Aspherical Lenslet Target) uses concentric rings of tiny aspheric lenslets to create a *volume* of non-focused light in front of the retina, rather than a single defocus plane. Stellest 2.0 upgrades this to **H.A.L.T. MAX**: - **Increased lenslet power and asphericity**, pushing the volume of non-focused light further from the retina and spreading it more widely — roughly twice the depth of signal. - **Twelve rings of lenslets instead of eleven**, and a wider 75 mm blank, which meaningfully widens frame choice. Essilor is careful to note that twice the signal depth does not mean twice the efficacy — a caveat worth repeating to parents. What the data says Stellest 2.0 was tested in a 12-month prospective, randomised, double-masked **contralateral crossover trial** in Singapore in 50 children aged six to ten. Each child wore a 2.0 lens in one eye and a first-generation Stellest in the other for six months, then swapped. - At six months, axial elongation was **0.043 mm in the 2.0 eyes versus 0.105 mm** in the first-generation eyes. - Over the full year, the cumulative difference was **0.107 mm less elongation** with 2.0, and **0.21 D less progression**. - No changes in binocular vision and no intervention-related adverse effects were reported. For context, the first-generation Stellest has two-year data showing around **71% reduction in progression and 53% reduction in axial elongation** against single vision, and six-year follow-up showing sustained effect. That long tail of evidence still belongs to the original lens, not to 2.0. Our honest read on the evidence Both lenses are genuine engineering advances, and the direction of travel — stronger signal, closer to the visual axis, wider coverage — is consistent across two independent manufacturers. That convergence is reassuring. But a few things deserve saying plainly: - **Both datasets are manufacturer-funded and short.** Twelve months is enough to show a signal, not enough to confirm a durable effect. Myopia control is a five- to ten-year project. - **The MiYOSMART iQ trial has been presented at conference but not yet fully peer reviewed.** We read it with the same caution we'd apply to any new lens. - **Stellest 2.0 was compared against Stellest, not against ordinary glasses.** That's an ethically sensible design, but it means the effect size is an *increment* on an already good lens. The crossover trial also had no washout period and no cycloplegia, which the authors themselves acknowledge. - **"No progression on average" is an average.** Some children in these trials still progressed. No lens is a guarantee. None of that is a reason to hold back. It is a reason to keep measuring — which is why axial length monitoring, not just refraction, sits at the centre of how we run myopia management. Which lens for which child? There is no head-to-head trial, so anyone claiming a clear winner is guessing. In practice the choice usually comes down to: - **Age at onset.** MiYOSMART iQ now has trial data down to age four, which matters for very early presenters. - **Rate of progression.** Fast progressors, and children who have progressed despite a first-generation lens, are the clearest candidates for either second-generation design. - **Frame choice and fit.** Both designs depend on accurate centration, and Stellest 2.0's wider blank helps with larger frames. Getting this right is not a detail — it's the difference between the treatment working and not. - **Whether spectacles are the right modality at all.** Contact lenses, orthokeratology and low-dose atropine remain part of the conversation, sometimes in combination. And whichever lens a child wears, the basics still count: full-time wear, **at least two hours outdoors a day**, and sensible near-work habits. Availability MiYOSMART iQ began reaching UK practices during 2026. Stellest 2.0 launched first in China in late 2025 with international rollout through 2026. Availability is moving quickly — if you'd like to know what we can fit right now, just ask. Talk to us If your child is short-sighted, or their prescription has changed since their last check, a myopia assessment gives you a proper baseline — including axial length measurement — and a clear plan. **Eyecare Opticians** 307 Richmond Road, Ham, Kingston upon Thames, KT2 5QU 020 8549 0331 *This article is for general information and isn't a substitute for a personal clinical assessment. Lens suitability is determined by your optometrist.*
by Eyecare Opticians • 16 March 2026
After examining more than 20,000 eyes over the past 20 years, certain patterns start to emerge. Patients often come in believing their vision is fine or that eye tests are simply about updating glasses. In reality, modern eye examinations have evolved dramatically since I first started practising. Thanks to significant investment in advanced technology, today’s eye examinations allow us to detect eye disease earlier and more accurately than ever before. Here are seven things many people misunderstand about their vision. 1. “My vision is fine, I don’t need an eye test.” Vision usually deteriorates very gradually. Most patients only realise how much their eyesight has changed when they put on their new glasses and suddenly see the world more clearly. Regular eye examinations are essential because changes can occur slowly without you noticing. 2. Eye Tests Are Not Just About Glasses Your eyes can reveal much more than your prescription. During a comprehensive eye examination we can sometimes detect early signs of conditions such as: Diabetes High blood pressure High cholesterol Neurological issues The eye is the only place in the body where we can directly observe blood vessels and nerves non-invasively. 3. Myopia in Children Is Increasing One of the biggest changes I have seen in practice is the rise in myopia (short-sightedness) in children. Modern lifestyles mean children spend more time indoors and on digital devices. Research shows that encouraging children to spend more time outdoors can reduce the risk of developing myopia. The encouraging news is that we can now slow the progression of myopia by around 50% over an eight-year period. Treatment options include: Orthokeratology (Ortho-K) – specially designed contact lenses worn overnight to gently reshape the cornea Specialist myopia control spectacle lenses designed to slow the growth of the eye Early intervention can significantly reduce the risk of eye disease later in life. 4. Many Serious Eye Conditions Have No Early Symptoms Many people assume they would notice if something was wrong with their eyes. Unfortunately, this is not always the case. Conditions such as glaucoma and macular degeneration often develop silently without symptoms in the early stages. This is why regular eye examinations are so important. 5. Technology Has Transformed Eye Examinations When I first started practising, we did not have access to the level of diagnostic technology we use today. With Optical Coherence Tomography (OCT), we can now examine the layers of the retina in extraordinary detail. This allows us to detect early signs of conditions such as: Glaucoma Age-related macular degeneration (ARMD) Retinal disease Often years before symptoms appear. 6. We Can See More of the Retina Than Ever Before Using Optomap widefield imaging, we can examine a much larger area of the retina compared with traditional methods. This means we can sometimes detect: Retinal holes Retinal tears Peripheral retinal changes Many patients have no symptoms at all, but identifying these problems early can prevent serious complications. 7. Early Detection Really Is Better Than Cure Perhaps the most important lesson from two decades of examining eyes is this: Early detection saves sight. Modern eye examinations are no longer simply about vision correction. They are about protecting eye health for the long term. Regular eye tests allow us to detect problems early and ensure the best possible outcome for our patients. Final Thoughts After examining thousands of eyes, one thing is clear: Looking after your eyes today helps protect your vision for the future. If it has been a while since your last eye examination, it may be time to book one. Your eyes may be telling a story you haven’t yet noticed.  📍 Eyecare Opticians Kingston upon Thames
by Nish Fofaria • 22 February 2026